Sunday, October 10, 2021

70yrs old farmer...

a 70yrs old male, farmer by occupation retieed two months ago came to the OPD c/o fever somce 8days, high grade with chills and cough which was productive and was relieved in 2days.
not associated with vomiting or loose stools, 
Fever was releived with treatment
pain in the abdomen, burning sensation since yesterday
not associated with chest pain, palpitations and pedal edema
thin stream of urine
deibbling+
increased frequency 
burning micturition
 pt is not a k/c/o DM, HTM, TB, asthma, epilepsy
6months back- UGIE was done for pain abdomen
retrosternal heart burn 
O/E- 
afebrile
PR- 76, irregularly, irregular
BP-100/50
RR- 22

CVS- S1 S2 +
RS- NVBS
Provisional diagnosis- Hypovolemic shock with MAT 
UTI- AKI
HFrEF- CAD

IVF- NS 50ml/hr
inj. nor ad 2amp with 47ml NS
inj lasix 40mg iv
inj dobutamine infusion 1 amp in 48ml.ns/hr (MAP greater than 60mm hg)
tab dolo 650 po/tid
Inj neomol 1gm iv temp greater than 101F
inj pan 40mg iv 
Fosfomycin satchet 
ECG during admission
ECG ON 11/10 AT 6:45
ECG AT 7AM
Patient developed SOB at 5:30 AM with saturations showing 67% at room air
Subjectively c/o cough with expectoration and respiratory distress

Objectively C/C distressed
BP -110/70 PR-120bpm irregular
Cvs-s1s2
Resp- fine end inspiratory crepitations in
B/L basal areas Wheeze- mid inspiratory in b/L ISA Cough with copious amount of sputum +

Assessment- ?AECOPD
Interventions done
Inj Hydrocortisone 100mg IV Inj Pheniramine maleate (Avil) 25mg IV
Nebulisation with budesonide and ipratropium bromide
After 30-40mins SOB subsided PR-90bpm regular.
Pt symptomatically feeling better

Soap notes day 2
ICU bed 4
Patient subjectively feeling better Cough and sob decreased when compared to yesterday 
Objectively
Bp 100/80 mm hg on 2 ml NA 
Pr: 76 bpm regularly regular 
Cvs: s1 s2 heard
Grbs 160 mg/dl
I/O: 1550/1200
Rs: Bae+ nvbs
P/a soft non tender
Assesment: Cardiogenic shock (resolving)with paroxysmal AF
Plan: Taper ionotropes
IVF NS 1AMP of optineuron
Inj monocef 1gm.iv bd
Inj pan 40mg iv bd
Inj neomol 1gm Iv T greater than 101F
Tab dilo 650 po sos 
SYP mucaine gel 10ml.po tid
Inj nor ad infusion(tapering) 
ECG ON 12/10/21


Soap notes day 3
Icu bed 4

Patient subjectively feeling better Cough and sob decreased when compared t...

Icu bed 4
Subjectively Patient is feeling better
No cough and sob

Objectively
Bp 90/60 mm hg on Nor adrenaline 4ml/hr
Pr 80 bpm
Rr 18 cpm
Grbs 170 mg/dl
Temp 97.5 F

Cvs s1 s2 
Rs bae, Nvbs
P/a soft nt

Assesment: Cardiogenic shock/ ? Septic shock (TLC 22,000) with paroxysmal AF

Plan Increase nor adr to maintain map 65 mm hg Taper iontrope once bp stabilises

AMC bed 3
Subjectivity patient is feeling better

Objectively
Bp 110/60 mm hg 
Pr- 55 bpm
Rr 20
Grbs 124 mg/dl
Temp 97.5 F
Cvs s1 s2
Rs bae, Nvbs
P/a soft nt

Assesment: Cardiogenic shock with
acute LV Failure secondary to MAT
MAT secondary to AECOPD
? viral pyrexia(resolved)
 
Plan- continue iv fluids 
inj. monocef 
inj Pan 40mg
inj neomol (if temp greater than 101F)

AMC bed 3

Subjectivity
patient complained of pain on left upper limb 

Objectively
Bp 110/70 mm hg 
Pr- 68 bpm
Rr 20
Grbs 78 mg/dl
Temp 97.8 F
Cvs- S1 S2 +
Rs BAE, Nvbs
P/a soft nt

Assesment: Cardiogenic shock with
acute LV Failure secondary to MAT
MAT secondary to AECOPD
? viral pyrexia(resolved)
 
Plan- continue iv fluids 
inj. monocef 
inj Pan 40mg
inj neomol (if temp greater than 101F)


Friday, October 1, 2021

Altered sensorium - SIADH

This is the second admission of the patient, the details of his  previous admission

45years man was brought to the casualty in an unresponsive state with fever and chills since 2days
On presentation, tonic posturing with frothing from mouth, fever and shivering
for seizures- inj lorazepam and levipill were given   HOPI- there was a decrease on appetite since 2days, pt was taken to the nearby RMP when he was given iv fluids, with no improvement in symptoms he was reffered here.
Similar complaints 15 days back with UTI, SEPSIS and resolved Alcohol withdrawal seizures   
Patient stopped working since 1 year (due to generalized weakness)
2 months back - pt had back pain (occasionally took pain killers).

H/O alcohol consumption since 15yrs(weekly thrice)
Zarda pan consumption - since 15 years Daily 1pack. 
No H/O smoking
Not a k/c/o DM, HTN, Asthma,TB, CAD
No H/o any past surgeries

On examination : 
Pt is unresponsive E1V1M4
No signs of pallor, icterus, cyanosis, clubbing, lymphadenoapathy, edema

Vitals:
temp- 101 F
PR: 90 bpm, regular
RR: 26 cpm
BP: 90/50 mmHg
SPO2: 
AT ROOM AIR 100%
Systemic examination :
 CVS:S1,S2 heard
 Apex beat:5th ICS
Resp:
BAE+
Nvbs heard
Position of trachea- central

P/A: soft, tenderness absent, bowel sounds heard

CNS examination 
Higher mental functions - 
GCS -  E1V1M4
Cranial nerves - 
Pupils - sliggish reacting to light ,mid dilated .
Dolls eye - present 
Gag reflex - intact 

Motor - 
Attitude of limbs - 
hypertonia in all four limbs 
Power couldn't be elicited as he is comatosed 
Spontaneous limb movements observed .
Reflexes -.             R                 L 
                  B.          2+.          2+
                 T          2+.          2+
                S          2+.          2+
                 K          2+.          2+
               A          2+.          2+

Plantars - bilateral extensor 
Sensory and cerebellar couldn't be ellicited
As patient is having fever spikes + ,meningeal signs+ 
LP was tried but couldn't get fluid .

EUVOLEMIC HYPOSMOLAR HYPONATREMIA  ?SIADH.
? BACTERIAL/TB MENINGITIS

 On lab evaluation he was found to be - severe hyponatremic - 
With sodium -117 (Deficit) 
serum osmolarity- 241
 urine electrolytes-
Cl- 182
Potassium- 16.4
Sodium- 142
management- 
 FLUID RESTRICTION <1 lit/day.
1 IN. LORAZEPAM acc/iv/stat
2 Inj. LEVIPILL 1000mg iv stat, 500mg iv Bd 
3 inj 3% NaCl iv 15ml/hr ( based on s/electrolytes)
4. Inj - OPTINEURON 1amp in 100ml N//IV/00
6. RT FEEDS 200ml milk with protein powder
6. IN. NORADRENALINE 2amp in 45ml NS / 4ml/hr( based on MAP 65mm hg
7. vitals monitoring - PR BP, GRBS, SPO2 4th hourly 

ICU bed 4
45yrs/male
SOAP NOTES DAY 1
Subjective
H/o fever spikes 

Objective
On examination :
Pt is c/c/c
No signs of pallor, icterus, cyanosis, clubbing, lymphadenopathy

Vitals:
TEMP 98.2F
PR: 92 bpm, regular
RR: 21cpm
BP: 100/70 mmHg
SPO2:
AT ROOM AIR-98%
GRBS:188mg/dl

Systemic examination :
CVS:S1,S2 heard Apex beat:5th ICS

Resp:
BAE+(vesicular breath sounds)
Nvbs heard
Position of trachea- central
P/A: soft, tenderness absent, bowelsounds hear
Cns:
HMF+
SPEECH-NORMAL
MEMORY-intact Pupils-NS RL
MOTOR
Power-(4/5 4/5)
 Tone-(Normal in all 4 limbs) Reflexes

    BTSAKP
R 2+ + + + flexion 
L 2++++flexion

Assessment
Altered sensorium secondary to ? Hyponatremia- ? SIADH

TB/ Bacterial meningitis With
pyrexia

Plan of care
head end elevation
inj levipil 800mg in bd inj 3% NaCl @ 25ml/hr
inj noradrenaline 2amp in 45ml NS 
inj optineuron 1amp
inj monocef 2 lgm iv
inj Vancomycin
Inj tolvaptan
 

ICU bed 4
45yrs/male
SOAP NOTES DAY 2
Subjective
H/o fever spikes 

Objective
On examination :
Pt is c/c/c
No signs of pallor, icterus, cyanosis, clubbing, lymphadenopathy

Vitals:
TEMP 98.2F
PR: 82 bpm, regular
RR: 21cpm
BP: 100/70 mmHg
SPO2:
AT ROOM AIR-98%
GRBS:145mg/dl

Systemic examination :
CVS:S1,S2 heard Apex beat:5th ICS

Resp:
BAE+(vesicular breath sounds)
Nvbs heard
Position of trachea- central
P/A: soft, tenderness absent, bowelsounds hear
Cns:
HMF+
SPEECH-NORMAL
MEMORY-intact Pupils-NS RL
MOTOR
Power-(4/5 4/5)
 Tone-(Normal in all 4 limbs) Reflexes

    BTSAKP
R 2+ + + + flexion 
L 2++++flexion

Assessment
Altered sensorium secondary to ? Hyponatremia- ? SIADH
TB/ Bacterial meningitis With
pyrexia

Plan of care
head end elevation
inj levipil 800mg in bd
 inj 3% NaCl @ 25ml/hr
inj noradrenaline 2amp in 45ml NS 
inj optineuron 1amp
inj monocef 2 lgm iv
inj Vancomycin
Inj tolvaptan

ICU bed 4
45yrs/male
SOAP NOTES DAY 3
Subjective
No fever spikes

Objective
On examination : 
Pt is c/c/c
Oriented to t/p/p
patient is able to talk and started oral feed 
No signs of pallor, icterus, cyanosis, clubbing, lymphadenopathy

Vitals:
TEMP 98.2F
PR: 90 bpm, regular
RR: 15cpm
BP: 110/80 mmHg 
SPO2:
AT ROOM AIR-99%
GRBS:101mg/dl
Systemic examination :
 CVS:S1,S2 heard
 Apex beat:5th ICS
Resp:
BAE+(vesicular breath sounds)
Nvbs heard
Position of trachea- central
P/A: soft, tenderness absent, bowel sounds heard
Cns: No focal deficit
HMF+
SPEECH-NORMAL
MEMORY-intact
No meningeal signs
Pupils-NS RL
MOTOR
Power-(4/5 4/5)
Tone-(Normal in all 4 limbs)
Reflexes-
     B T S A K P 
R 2+ + - + + flexion
 L 2+ + - + + flexion

Assessment-
Altered sensorium secondary to ? Hyponatremia- ? SIADH
TB/ Bacterial meningitis With
pyrexia

 
Plan of care-
 head end elevation 
inj levipil 800mg in bd
inj optineuron 1amp 
inj monocef 2 lgm iv
inj Vancomycin 500mg in 200ml NS
Inj Neomol 1gm iv sos 
tab pcm 650mg 
tab tolvapt 15mg
double strength Ors 
monitoring vitals 4th bourly 
.Monitor vitals-4rth hourly
  I/O charting
AMC bed 7
45yrs/male
SOAP NOTES DAY 5
Subjective
No fever spikes

Objective
On examination : 
Pt is c/c
Oriented to t/p/p
No signs of pallor, icterus, cyanosis, clubbing, lymphadenopathy

Vitals
PR: 86 bpm, regular
RR: 15cpm
BP: 90/70 mmHg 
GRBS: 120 mg/dl
Systemic examination :
 CVS:S1,S2 heard
 Apex beat:5th ICS
Resp:
BAE+(vesicular breath sounds)
Nvbs heard
Position of trachea- central
P/A: soft, tenderness absent, bowel sounds heard
Cns: No focal deficit
HMF+
SPEECH-NORMAL
MEMORY-intact
No meningeal signs
Pupils-NS RL
MOTOR
Power-(4/5 4/5)
Tone- 
Reflexes-
     B T S  K A P 
R  2+ 2 +1+3  -withdrawal
L  2 +2 +1 +2 - withdrawal

Assessment-
Altered sensorium secondary to ? Hyponatremia- ? SIADH
TB/ Bacterial meningitis With
pyrexia

 Plan of care-
 head end elevation 
inj levipil 800mg in bd
inj optineuron 1amp 
inj monocef 2 lgm iv
inj Vancomycin 500mg in 200ml NS
Inj Neomol 1gm iv sos 
inj lorazepam 2cc i.v SOS
tab pcm 650mg 
double strength Ors 
monitoring vitals 4th bourly 
Monitor vitals-4rth hourly
 I/O charting

Lumbar puncture was performed and CSF analysis was done to rule out TB MENINGITIS and arachnoiditis
Ward case
45yrs/male
SOAP NOTES DAY 7
Subjective
No fever spikes

Objective
On examination : 
Pt is c/c
Oriented to t/p/p
No signs of pallor, icterus, cyanosis, clubbing, lymphadenopathy

Vitalss
PR: 78 bpm, regular
RR: 15cpm
BP: 100/70 mmHg 
GRBS: 116 mg/dl
Systemic examination :
 CVS:S1,S2 heard
 Apex beat:5th ICS
Resp:
BAE+(vesicular breath sounds)
Nvbs heard
Position of trachea- central
P/A: soft, tenderness absent, bowel sounds heard
Cns: No focal deficit
HMF+
SPEECH-NORMAL
MEMORY-intact
No meningeal signs
Pupils-NS RL
MOTOR
Power-(4/5 4/5)
Tone- 
Reflexes-
     B T S K A P 
R 2+ 2 +1 +2 - withdrawal
L 2 +2 +1 +2 - withdrawal

Assessment-
Euvolemic hyposmolar Hyponatremia
SIADH with hyponatremic seizures

 Plan of care-
 head end elevation 
inj levipil 800mg in bd
inj monocef 1gm bd
inj Vancomycin 500mg in 200ml NS
Inj Neomol 1gm iv sos 
inj lorazepam 2cc i.v SOS
tab pcm 650mg 
double strength Ors 
monitoring vitals 4th hourly

Monday, April 26, 2021

General Medicine- Short Case

 Hall ticket no. 1601006126

This is an online e logbook to discuss our patients deidentified health data shared after taking her/guardian's signed informed consent

Here we discuss our individual patient problems through series of inputs from available global online community of experts with an aim to solve those patients clinical problems with collective current best evidence based input.

This E log also reflects my patient centre’s online learning portfolio and valuable inputs on the comment box is welcome.

Case- 

A 55 years old man, resident of Nalgonda farmer by occupation came to the OP with chief complaints of- 

-Swelling in both the legs 

-Reduced urine output 

History of Presenting Illness

Patient was apparently asymptomatic 10 days ago then he noticed bilateral pedal edema developed gradually and decreased urine output.

No h/o fever, burning micturition, hematuria

No h/o of chest pain, cough, expectoration , hemoptysis, reccurent respiratory tract infections.

 No h/o palpitations, syncope.

No history suggestive of hypo or hyperthyroidism.

Past medical History- he is a known case of Hypertension 

He is not a known case of diabetes mellitus, bronchial asthma, thyroid disorders, epilepsy, coronary artery disease. 

Personal history :   

-consumes mixed diet 

- appetite is reduced

-sleep- adequate

-Bowel movements regular

-bladder habits irregular 

Consumes alcohol occasionally

-No habit of smoking and tobacco and Pan chewing 

Family history:- 

No significant family History

Treatment history:- he is on antihypertensive medication. 

General Examination

Patient is conscious, coherent and cooperative. 

He is moderately built and nourished. 

He has no signs of pallor, icterus, clubbing, koilonychia, b/l pedal edema is present


Pulse rate- 98bpm

Respiratory rate- 18/min

Blood pressure- left arm- 130/90mm hg 

Cardiovascular examination- 

S1 and S2 heard. 

No thrills and murmurs 

Respiratory system examination- 

Bilateral air entry presents, vesicular breath sounds + 

No dyspnea, wheezing

Position of trachea- Central 


ABDOMEN

Shape of abdomen - Scaphoid

No Tenderness 

No Palpable mass

Hernial Orifices - Normal

No Free Fluid 

No Bruits 

Liver Not palpable  

Spleen - Not palpable

Investigations:- 


Ultrasonography finding- Renal parenchymal disease of grade- 2.


Provisional Diagnosis: Chronic Kidney Disease etiology- secondary to systemic Hypertension. 

Management:- 

Tablet- Laxix 40mg 

Tablet- Nicardia 20mg 

Tablet- Met xl 

Tablet- Nodosis 

Tablet-  Arkamine 

Tablet- human atropine. 

With respect to renal failure, compensated by regular hemodialysis. 


Sunday, April 25, 2021

General Medicine Final Exam- Long Case-

Hall ticket no. 1601006126

This is an online e logbook to discuss our patients deidentified health data shared after taking her/guardian's signed informed consent
Here we discuss our individual patient problems through series of inputs from available global online community of experts with an aim to solve those patients clinical problems with collective current best evidence based inputs

This E log also reflects my patient centre’s online learning portfolio and valuable inputs on the comment box is welcome.

Case Presentation of Upper motor neuron lesion who is also a known case of diabetes and hypertension.

A 50 years old female, from Suryapet who is a homemaker was brought to the OP as she was unable to lift her left arm and left leg. and her mouth was deviated to right side since 3 days.

History of Presenting Illness
The patient was apparently asymptomatic 7 days ago, then she felt dizzy for a brief period of time.

3 days ago, she felt weakness during morning hours in her left arm while making breakfast and noticed weakness in her left leg followed by fall on the floor. 

Weakness was sudden in onset and rapidly progressed to a state where she was unable to move her left side of the body. 

There were no similar attacks in the past.
There was no history of headache, nausea, vomiting, fever or burning micturition and she is not a known case of migraine.

No sensory impairment, no dysphagia, no giddiness, no tinnitus, no hearing impairment, no visual disturbance, no bowel and bladder incontinence and no new gait abnormality

Past medical history
She is a known case of diabetes mellitus since 5years and Hypertension since 3 years for which she was on medication.
Glimipramide 0.2mg 
Voglibose 0.2mg and 
tenegliptin 20mg 
Metformin 500mg 
Telmesartan 40mg 
Amlodipine 125mg. 

She is not a known case of Tuberculosis, bronchial asthma, thyroid disorders, epilepsy.

Menstrual history
She had undergone hysterectomy 4 years ago for fibroid uterus

Family history:- No significant history.

Personal history 
she has mixed diet
Normal appetite.
Bladder habits are regular.
bowel movements are irregular.
she has not been able to pass stools since 5 days. 
No allergic reactions to any known drugs


General Examination:- 
The patient was conscious cooperative oriented to the time place and person and cooperative lying on the bed in supine position. 
Patient was afebrile
Pulse = 69 beats per minute.
- Blood pressure = 140/70 mm of Hg.
- Respiratory rate = 16 cycles per minute.
- JVP is not elevated
- There is NO Pallor, Icterus, Clubbing, Cyanosis, Generalized lymphadenopathy and Edema.

Nervous system examination
the patient is conscious, alert, oriented and cooperative.
Higher mental function is intact and presence of slurring of speech. 
Right handedness

Cranium and spine- no abnormalities detected.
Signs of meningeal irritation- neck rigidity, Kernig's, Brudzinski are negative 
there is no kinking or bruits in carotid arteries.

Cranial nerves examination:- 
Pupils- left and right reactive to light 
3rd, 4th, 6th no abnormalities
5th nerve- sensory- normal 
                               - motor- jaw jerk +ve 
7th nerve- mouth deviation towards- right
  Drooling of contents of food from left side
 frowning present
-absent nasolabial folds on left side
-blowing and whistling absent


Taste sensation on anterior 2/3rd of tongue present
Corneal reflex present on both sides

Vestibulocochlear nerve- Rinnes Weber, Schwabach test normal on both sides

9th, 10th, 11th- gag reflex +


Motor function- 
Nutrition- normal- no wasting seen on both sides

Tone- right upper limb- normal
            Right lower limb- normal
            Left upper limb- normal 
            Left lower limb- normal
Power- right upper limb- 5/5
            Right lower limb- 5/5
            Left upper limb-  0/5
            Left lower limb- 0/5

Reflexes:-                       Right               left

  i) Superficial Reflexes 

. Corneal reflex          present         present
. Conjunctival reflex present       present
. Plantar reflex          flexor             extensor

   ii) Deep Reflexes
                       Right          left
Biceps              +2              +3
Triceps              +2          +3
Supinator         + 2           +3
Knee                 +2             +3              
Ankle.                Not elicited              
Plantar              flexor    Extensor

Sensory system  
Superficial -fine touch,temperature, pain -present

Deep-position, vibration, crude touch, stereognosis, 2point discrimination- present 

Cerebellum- Speech, nystagmus, tremors- absent

Coordination
Finger nose test ,finger finger test,heel knee test-present


Cardiovascular system- S1 and S2 heard no murmurs, not a known case of valvular heart disease atrial fibrillation

Respiratory system- Bilateral air entry present

Respiratory-Normal vesicular breath sounds,bilateral air entry present

GIT -no significant findings

Provisional Diagnosis-
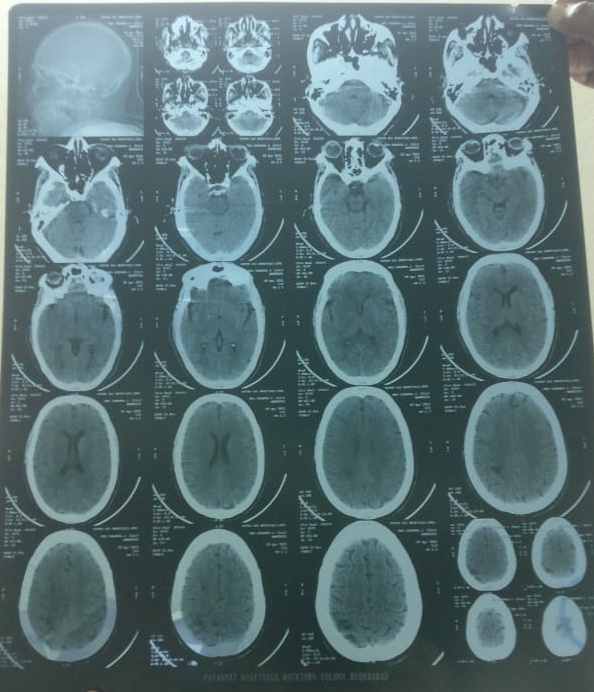
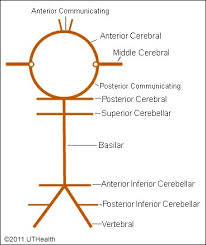
Left Sided hemiparesis with left UMN type of facial paresis (due to right middle cerebral artery infarct)


Medical Management- 
Aspirin 75mg 
Clopidogrel 75mg 
Pantoprazole 40mg 
Atorvastatin 40 mg
Physiotherapy 
GRBS monitoring 8th hourly.